


On this page
- What Is DSO RCM Staffing Optimization?
- The Hidden Cost of Manual Billing Across a Growing DSO Portfolio
- Three Models for Enterprise DSO RCM: A Head-to-Head Comparison
- Enterprise Implementation Roadmap: From Pilot Site to Full DSO Deployment
- ROI Reality Check: What DSO CFOs Actually Achieve
- Your Next Move: The 90-Day DSO RCM Transformation Plan
Your DSO just closed on eight new practices. The integration playbook is thick, the payer mix is messy, and your revenue cycle team is already stretched across 60 locations. Do you post another dozen remote billing coordinator roles — or deploy AI agents that start executing claim status checks on day one?
This is the defining staffing question for DSO executives in 2026. The answer is rarely one or the other, but finding the right ratio of human expertise to AI automation determines your cost-per-claim, your M&A integration speed, and ultimately your EBITDA multiple.
This guide gives you a structured framework for making that decision at enterprise scale — complete with head-to-head comparisons, real deployment data, and a 90-day action plan you can bring to your next board meeting.
What Is DSO RCM Staffing Optimization?
DSO RCM staffing optimization is the discipline of right-sizing your revenue cycle workforce — balancing remote human teams, onshore specialists, and AI-driven automation — to maximize net collections while minimizing cost-per-claim across a multi-location dental portfolio. At its core, it answers a resource-allocation question: which RCM tasks should be performed by humans, and which should be delegated to autonomous AI agents?
For growing DSOs, this question has direct financial consequences. Labor typically accounts for 60–70% of total RCM operating costs, and every unnecessary FTE erodes the margin expansion that private equity sponsors expect post-acquisition. At the same time, under-staffing creates AR backlogs, missed filing deadlines, and denial write-offs that quietly bleed millions in recoverable revenue.
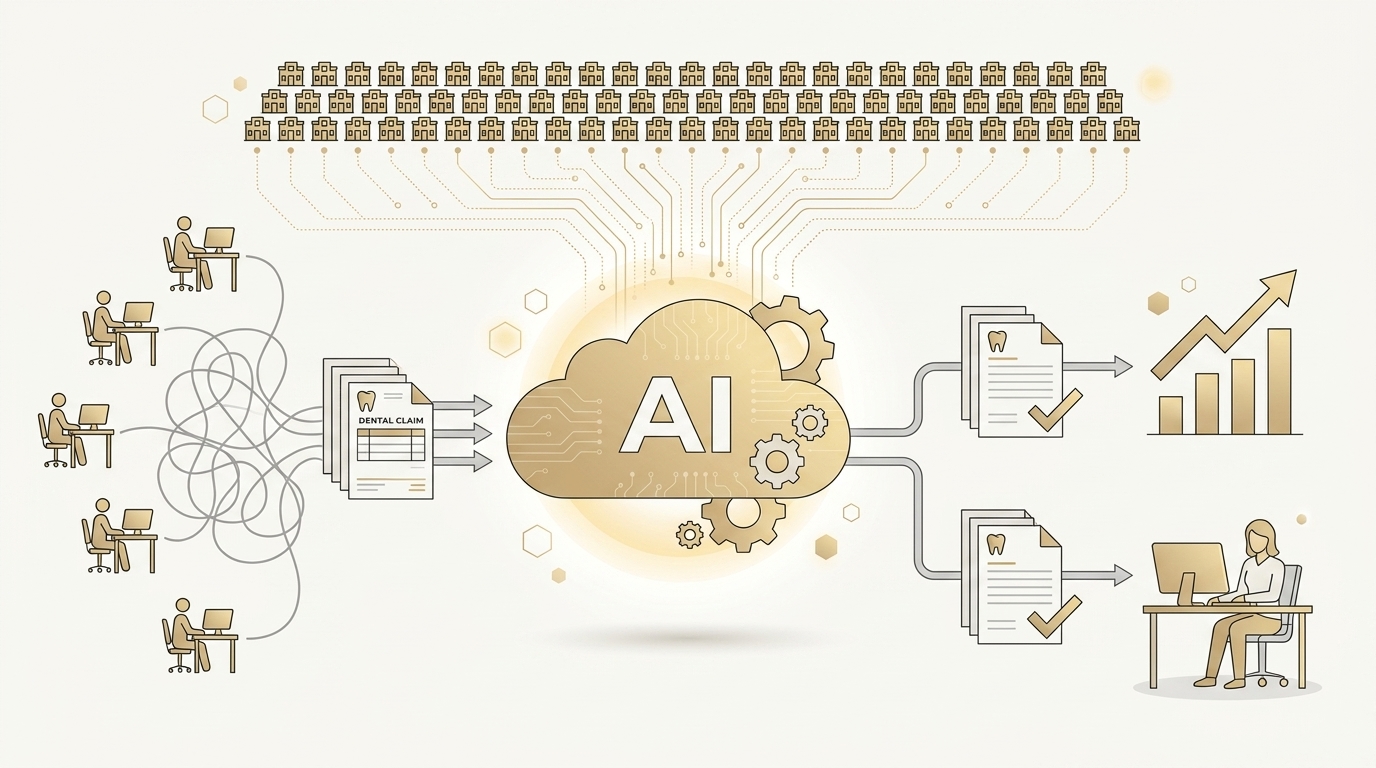
The most successful DSOs in 2026 are deploying a hybrid model. Smilist, a 116-office DSO, deployed Ventus AI for claim statusing across their portfolio. AI agents now execute over 3,000 status checks per day — volume that would require a team of 5–8 dedicated coordinators. Human team members, meanwhile, focus on complex appeals, patient escalations, and payer relationship management.
This article breaks down the three primary DSO RCM staffing models, compares them across seven enterprise metrics, and provides an implementation roadmap for executives ready to act.
The Hidden Cost of Manual Billing Across a Growing DSO Portfolio
Remote RCM teams were a revelation during the post-2020 talent shift. DSOs could recruit billing coordinators from lower-cost markets, avoid office overhead, and scale headcount faster than in traditional on-site models. But by 2026, the cracks in a remote-only approach have become impossible to ignore at enterprise scale.
Recruiting and Retention Drag
The average turnover rate for remote dental billing staff hovers between 30–40% annually, according to MGMA and HFMA benchmarks. For a DSO with 75 locations running a 25-person remote billing team, that means replacing 8–10 coordinators every year. Each replacement cycle costs $4,000–$7,000 in recruiting, credentialing, and ramp-up time — not including the productivity gap while a new hire gets up to speed on your specific payer mix and workflows.
Inconsistency Across Locations
When you acquire a new group of practices, each one arrives with its own billing habits, clearinghouse configurations, and denial patterns. Remote teams struggle to standardize processes across a heterogeneous portfolio. A coordinator trained on Delta Dental in the Southeast may stumble on MetLife nuances in the Midwest. The result is variable claim denial rates across regions — some offices sitting at 8%, others at 18% — with no systematic way to close the gap.
Scale Creates Diminishing Returns
Adding the 30th remote coordinator doesn't deliver the same marginal value as the 5th. Supervision costs rise. Communication overhead increases. Quality audits become harder. You're scaling a labor-intensive process linearly while your location count — and claim volume — is growing exponentially through acquisition.
The M&A Integration Bottleneck
Perhaps the sharpest pain point for PE-backed DSOs: every new acquisition adds 60–120 days of RCM integration work. Payer enrollment, fee schedule loading, ERA/EFT setup, and historical AR cleanup all demand human attention. If your remote team is already at capacity, new acquisitions sit in billing limbo, directly impacting your post-close revenue realization.
These challenges don't mean remote teams are obsolete — far from it. They mean the ratio of human-to-automated work needs to shift, and shift intelligently.
Ventus for multi-location groups
Tend removed 50% of its outsourced verification load in two months across 33 locations.
Book a DemoThree Models for Enterprise DSO RCM: A Head-to-Head Comparison
DSO leaders evaluating their 2026 staffing strategy generally face three paths. Here's how each one stacks up.
1. Fully Remote Human Team
Best for: DSOs under 20 locations with stable payer mixes and low acquisition velocity.
- Pros: High flexibility for complex cases; institutional knowledge builds over time; easier to manage escalations involving patient communication.
- Cons: High turnover risk; linear cost scaling; inconsistent quality across locations; slow M&A integration; supervision overhead compounds with team size.
2. Outsourced RCM (Third-Party Billing Company)
Best for: DSOs that want to offload RCM entirely and accept reduced visibility into day-to-day operations.
- Pros: Shifts management burden to vendor; often includes technology stack; contractual SLAs.
- Cons: Margin erosion (typical fees range from 5–9% of collections); limited customization; black-box reporting; vendor lock-in; loss of institutional data and payer relationships.
3. AI Agent-Augmented Hybrid Model
Best for: DSOs with 50+ locations seeking standardized, scalable RCM with reduced cost-per-claim and faster M&A integration.
- Pros: AI agents handle high-volume, rules-based tasks 24/7 (claim statusing, insurance verification); human team focuses on appeals, complex denials, and relationship management; rapid deployment at new locations; consistent execution across entire portfolio.
- Cons: Requires change management; humans still needed for judgment-intensive work; initial configuration effort (though typically under 7 days with Ventus).
Enterprise Comparison Table
| Metric | Fully Remote Human Team | Outsourced RCM Vendor | Ventus AI Agents + Lean Human Team |
|---|---|---|---|
| Cost per claim | $4.50–$7.00 | 5–9% of collections | $1.50–$3.00 |
| Scalability | Linear (add FTEs) | Vendor-dependent | Near-instant (add workflows) |
| M&A integration speed | 60–120 days | 45–90 days | 7–14 days for core claim tasks |
| Annual turnover risk | 30–40% | Vendor manages | 0% for AI agents |
| Hours of operation | 8–10 hrs/day | 8–12 hrs/day | 24/7 autonomous execution |
| Quality consistency | Variable by coordinator | Contractual SLA | Deterministic — same process every time |
| Visibility & audit trail | Manual QA sampling | Limited (vendor-controlled) | Full audit trail, real-time dashboards |
| HIPAA compliance | Training-dependent | Vendor BAA | SOC 2 Type II + BAA |
The hybrid model — AI agents handling repeatable volume while a lean, skilled human team manages exceptions — consistently delivers the strongest cost-per-claim and integration speed metrics for DSOs operating at 50+ locations.
Enterprise Implementation Roadmap: From Pilot Site to Full DSO Deployment
Deploying AI agents across a multi-location DSO isn't a rip-and-replace event. It's a phased rollout designed to prove value quickly, build internal confidence, and expand systematically.
Phase 1: Pilot Site Selection (Week 1)
Choose 3–5 representative locations. Ideal pilot sites have a mix of commercial and Medicaid payers, moderate denial rates (10–15%), and a cooperative office manager. The goal is to validate AI agent performance on your actual payer portals and claim volumes.
Ventus AI agents work via browser-native automation — no API integrations, no clearinghouse reconfiguration. They log into the same payer portals your team uses, handle MFA and CAPTCHAs, and execute bulk claim status checks at machine speed.
Phase 2: Parallel Run and Validation (Weeks 2–3)
Run AI agents alongside your existing team for two weeks. Compare output: accuracy rates, turnaround times, exception rates. This parallel run builds trust with your RCM director and surfaces any payer-specific quirks that need workflow adjustments.
"Ventus stands out from the noise in the AI and automation market. Their approach allows them to ramp up quickly in the messy middle of RCM."
— Philip Toh, Co-founder & President, Smilist
Smilist used this parallel approach across their growing portfolio. Within the first two weeks, AI agents were executing over 3,000 claim status checks daily with accuracy rates that matched or exceeded their human coordinators — at a fraction of the cost.
Phase 3: Workforce Rebalancing (Weeks 3–4)
Once validated, begin shifting your human team. This isn't about layoffs — it's about redeployment. Move your best coordinators from repetitive status checking into high-value roles:
- Complex denial appeals: Where clinical narrative and payer-specific strategy matter
- Patient account resolution: Calls that require empathy and negotiation
- New location onboarding: Leveraging institutional knowledge during M&A integration
- Payer relationship management: Escalation calls that require relationship context
Phase 4: Portfolio-Wide Rollout (Weeks 4–8)
Expand AI agents to all locations in waves of 10–15 sites. Each wave takes 2–3 days to configure because the browser-based automation adapts to the same portals your team already uses. Ventus agents communicate exception alerts via Slack, Teams, or Email and can even make phone calls to payers to resolve specific exception scenarios.
Common Pitfalls to Avoid
- Piloting too small: A single-location pilot won't reveal multi-location scaling dynamics. Start with 3–5 sites minimum.
- Skipping change management: Your RCM team needs to understand that AI agents are teammates, not replacements. Communicate the redeployment plan early.
- Ignoring audit trails: Ensure every AI action is logged and auditable. Enterprise security and compliance aren't optional — they're a requirement for DSO boards and PE sponsors.
- Waiting for perfect data: Your data will never be perfectly clean. AI agents are designed to operate in what Philip Toh calls "the messy middle of RCM."
ROI Reality Check: What DSO CFOs Actually Achieve
The financial case for AI-augmented RCM is compelling, but DSO CFOs rightly demand specifics. Here's what the numbers look like at enterprise scale, grounded in real deployment data and industry benchmarks.
Direct Cost Savings
- FTE reduction on repetitive tasks: A 75-location DSO running 15 remote coordinators on claim statusing can typically reduce to 4–6 coordinators handling exceptions only. At a fully loaded cost of $45,000–$55,000 per remote FTE, that's $400,000–$600,000 in annual savings.
- Turnover cost elimination: Zero turnover on AI agents means zero recruiting, onboarding, or ramp-up costs for automated workflows. For a team of 15, that's an additional $40,000–$70,000 annually.
- Overtime and surge staffing: AI agents don't require overtime during open enrollment surges or post-acquisition AR cleanup sprints.
Revenue Acceleration
- Faster claim resolution: Statusing 3,000+ claims per day vs. 150–200 per human coordinator means AR days shrink by 15–30 days across the portfolio.
- Denial identification speed: AI agents flag denials within hours of posting, not days or weeks. Earlier intervention means higher overturn rates.
- Portfolio-wide revenue recovery: DSOs deploying AI agents for claim statusing and denial management typically recover an incremental 2–4% of net collections — translating to $500K–$2M+ annually for a 75-location portfolio.
Valuation Impact
- EBITDA improvement: Reducing RCM labor costs by $500K+ while simultaneously recovering $1M+ in previously written-off revenue directly increases EBITDA — a metric that drives DSO valuation multiples.
- Standardization premium: PE buyers pay more for DSOs with consistent, automated RCM processes because they de-risk post-acquisition integration.
Timeline to Results
- Quick wins (Week 1–2): Pilot sites processing 500+ claim status checks per day with full audit trails.
- Measurable savings (Month 2): First wave of FTE rebalancing complete; cost-per-claim trending downward.
- Full portfolio impact (Month 3–4): All locations live; AR days declining; denial identification accelerated across the portfolio.
Use the Ventus ROI calculator to model the specific impact based on your location count, payer mix, and current FTE structure.
Your payers. Your systems.
One central setup. Multi-location groups go live in about a month.
Book a DemoYour Next Move: The 90-Day DSO RCM Transformation Plan
The staffing decision isn't binary — it's about finding the right ratio of human expertise to AI execution for your specific portfolio. Here's how to start.
- Days 1–7: Audit your current state. Map every RCM FTE to their primary tasks. Identify the top 3 highest-volume, most repetitive workflows (claim statusing is almost always #1). Calculate your current cost-per-claim and denial rate by region.
- Days 8–21: Run a focused pilot. Select 3–5 locations with representative payer mixes. Deploy AI agents on claim statusing and insurance verification. Measure accuracy, throughput, and exception rates against your human baseline.
- Days 22–45: Validate and rebalance. Review pilot data with your CFO and RCM director. Model the portfolio-wide savings using the ROI calculator. Begin redeploying human coordinators from statusing to appeals and complex denial work.
- Days 46–90: Scale across the portfolio. Roll out AI agents in waves of 10–15 locations. Standardize workflows, reporting, and escalation protocols. Celebrate the first quarter where your cost-per-claim drops and your net collection rate rises simultaneously.
The DSOs winning in 2026 aren't choosing between people and technology. They're building hybrid teams where AI agents handle the volume and humans deliver the judgment. The question isn't whether to make this shift — it's how fast you can execute it.
→ See how it works on your payer mix — Book a 30-minute demo
Explore more dental RCM articles and customer stories to see how DSOs at every stage of growth are deploying AI agents across their revenue cycle.